Visual Prosthesis — Combined Overview (Retina + Optic Nerve + LGN + Cortex)
Umbrella hub for the visual-prosthetics family of brain-computer-interface. Any implantable system that replaces lost photoreceptors/optic-path function to restore vision — whether it interfaces the residual retina, the optic nerve, or the visual cortex itself.
The two families
| Retinal prostheses | Cortical (cortex) prostheses | |
|---|---|---|
| Target | Retina (epiretinal / subretinal / suprachoroidal) | Visual cortex (V1; surface, intracortical, or LGN) |
| Principle | Stimulate surviving bipolar/RGCs | Stimulate neurons to elicit phosphenes |
| Requirement | Healthy inner retina (bipolar/RGCs) | Intact visual cortex only — bypasses eye and optic nerve |
| Indications | GA / AMD, RP, Stargardt | Any cause of blindness incl. optic-nerve damage; totality of blindness |
| Resolution (2026) | PRIMA 378 px; form vision demonstrated (reading) | Orion 60 ch (phosphene vision, 6-yr data); 1,000+ ch in animals (1024-ch monkey study) |
| Maturity | Commercial (PRIMA, CE-marked EU 2026) | Clinical/preclinical (No commercial device yet) |
| Pages | retinal-prosthesis, retinal-prosthesis-companies | cortical-visual-prosthesis, cortical-visual-prosthesis-companies |
Optic-nerve stimulation
The 2025 Biomedical Engineering Letters review (Kim & Seo) frames artificial-vision prostheses as targeting four sites on the visual pathway — retina, optic nerve, LGN, and visual cortex — of which the retina remains the most accessible target and the optic nerve the most anatomically constrained.1
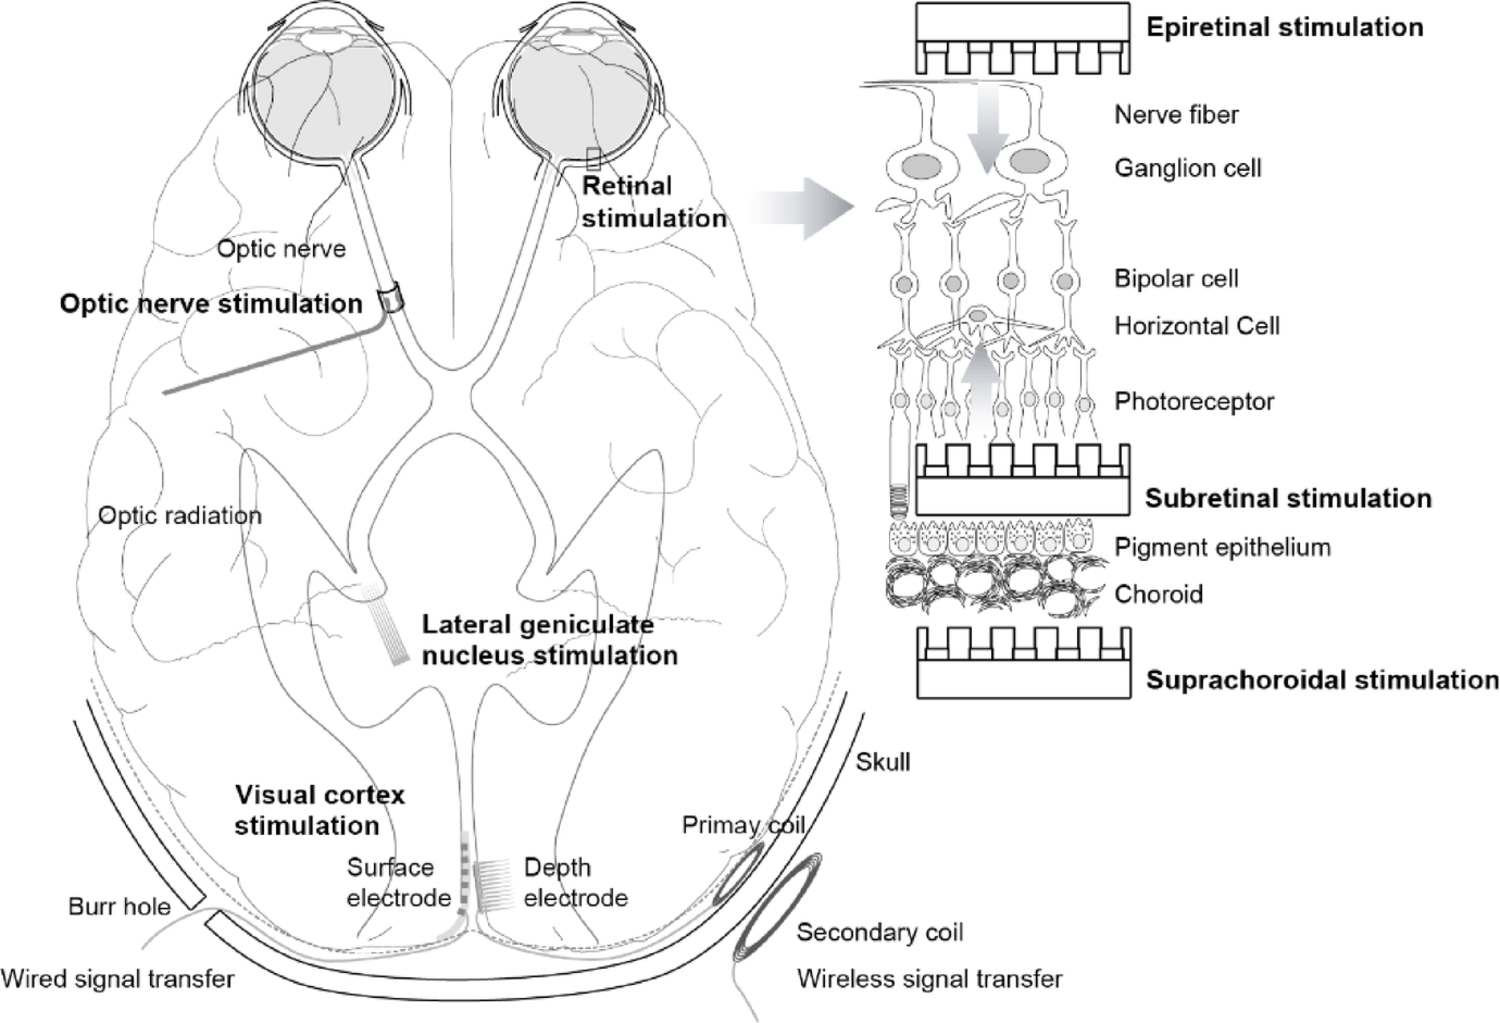
Fig. 1 from Kim & Seo (2025) — visual-information processing and the four stimulation sites of artificial vision: retinal cross-section with electrode implantation targets, plus the optic-nerve, LGN, and cortical routes. CC BY 4.0.
The optic nerve crams ~1.2 million retinal ganglion-cell axons into a 4–5 mm bundle that must be approached through the bony optic canal — a neurosurgical route that caps the achievable spatial resolution. Three electrode strategies have been explored:1
- Extraneural cuff — a self-sizing spiral cuff around the nerve. Veraart’s chronic human implant (RP volunteer) produced parameter-dependent, topographically distributed phosphenes; later intraorbital placement enabled 4- and 8-contact arrays with current steering, and training supported object localisation, discrimination, and reach-to-grasp.
- Intraneural / penetrating arrays — depth-dependent visuotopic mapping in cats, and the OpticSELINE array (rabbits), which produced spatially selective V1 activation (ECoG) — evidence that intraneural arrays can exceed cuff selectivity.
- Optic-disc implants (AV-DONE, Nidek) — fine platinum wires (≈50 µm) inserted into the nerve head produced localised phosphenes at thresholds of ~5–70 µA; a 7-wire iteration targets more channels via a single vitreous entry.
Evidence remains pilot-scale: no optic-nerve device approaches the channel counts or clinical maturity of the retinal systems, and the review positions the route as an alternative for severe retinal degeneration where photoreceptors and inner retinal layers are largely nonfunctional.1
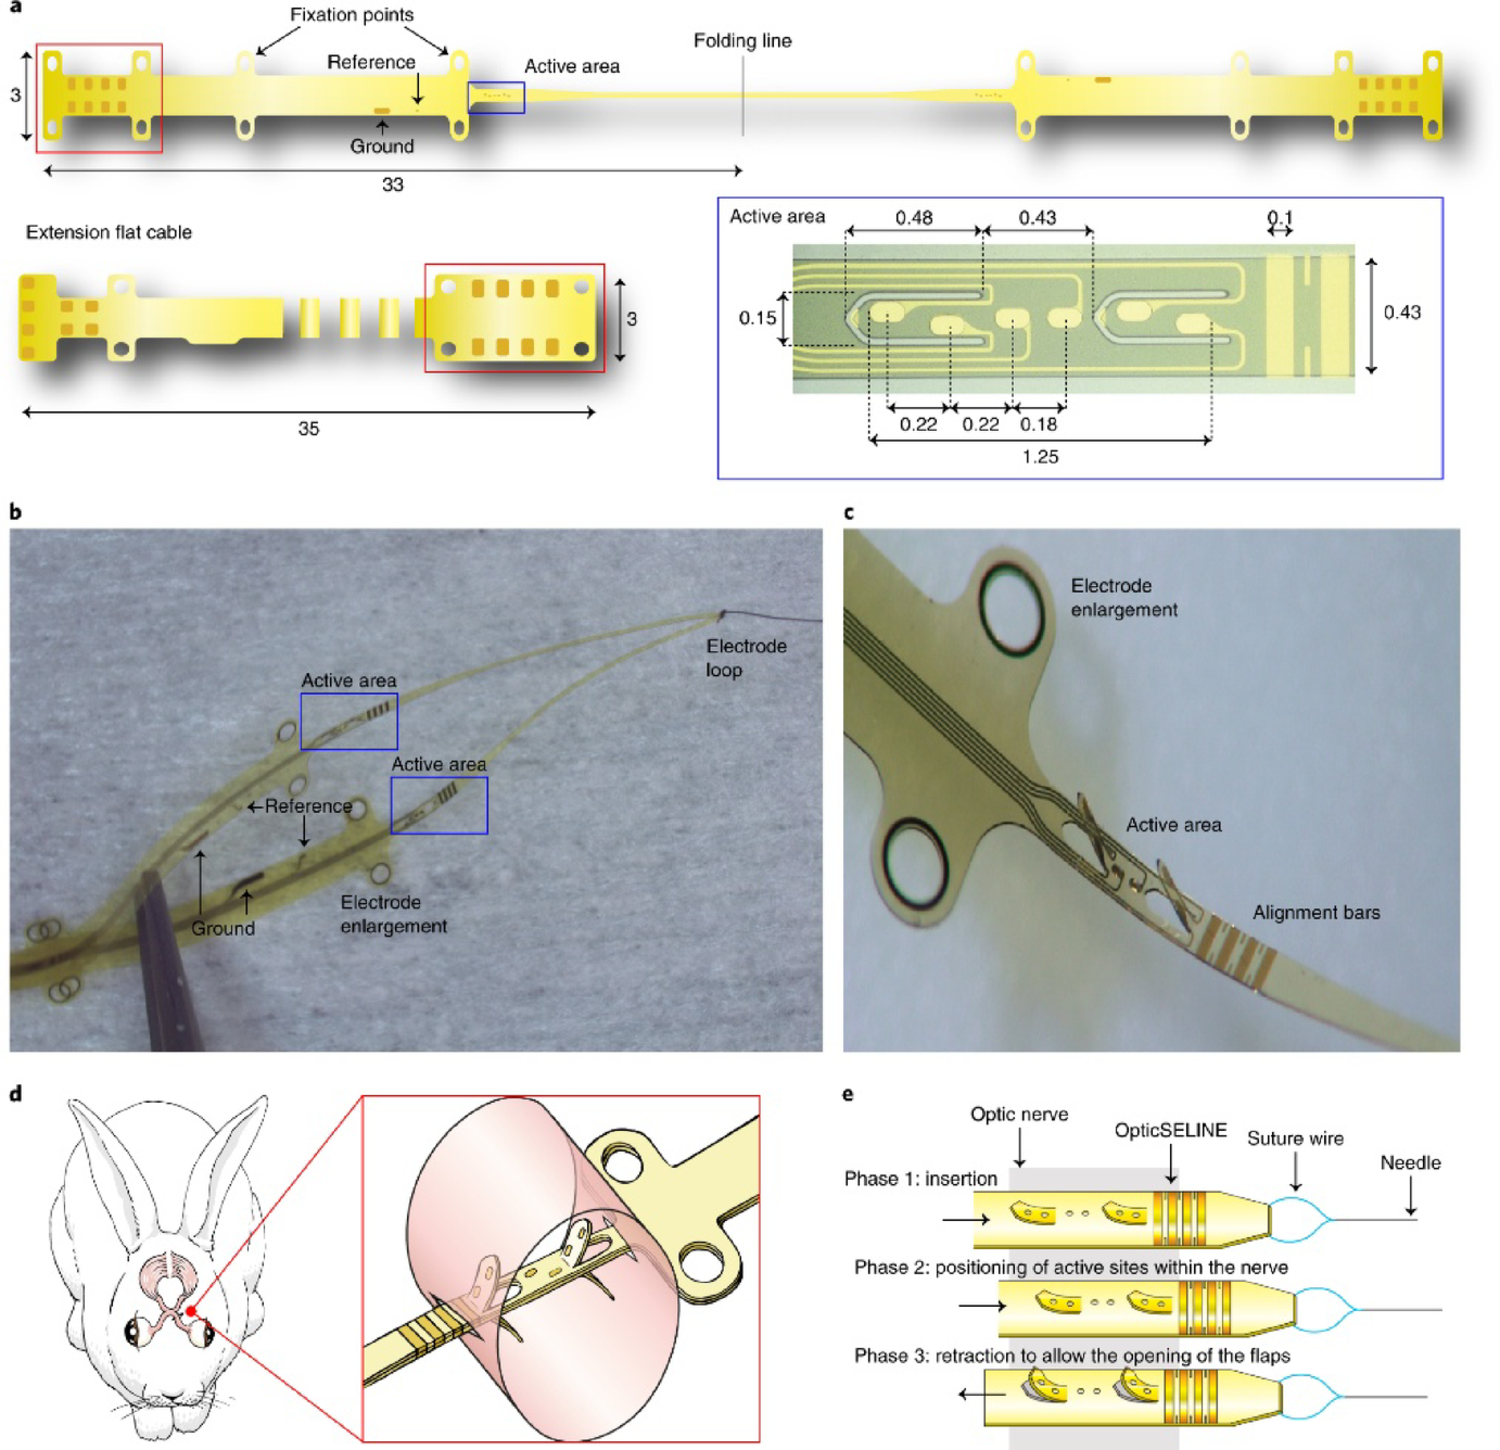
Fig. 7 from Kim & Seo (2025) — the OpticSELINE intraneural optic-nerve implant: device layout, electrode loop, placement at the optic disc, and the suture-wire insertion sequence. CC BY 4.0.
Shared design language
All modern systems converge on the same architecture: **camera glasses + processor
- wireless power/telemetry + electrode array** (or photovoltaic chip), producing phosphene-based artificial vision. Key concepts: form vision (integration of elements into percepts — first demonstrated by PRIMA; also via dynamic stimulation in cortex), topographic phosphene mapping, and visual learning (the brain must learn to interpret stimulation).2
The archetypal implementation is still the Argus II (Second Sight; the first FDA-approved retinal prosthesis, 2013): camera glasses → portable video processor → wireless link → a 60-electrode array on the macula — the template nearly every later system reuses.1
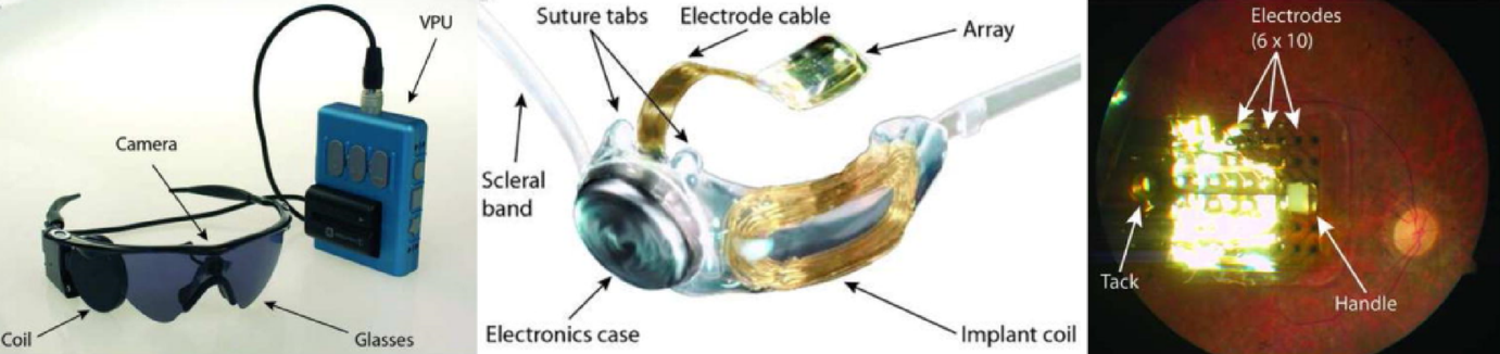
Fig. 2 from Kim & Seo (2025) — the Argus II system: glasses-mounted camera, coil and video processing unit (A); the implanted receiver and electrode array (B); and the epiretinal array tacked over the macula (C). CC BY 4.0.
Strategic debate: retina-first vs cortex-universal
- Retina-first (science-corp/max-hodak): simple structure, controllable surgery, clear population (GA/AMD >5M), fastest regulatory + commercial path — the only approach with a CE-marked, commercially available form-vision device (Jul 2026).
- Cortex-universal (neuralink Blindsight, ReVision Implant, Monash Gennaris): universal applicability (“performance trumps invasiveness” — every completely blind person spoken to said they don’t mind where the implant goes, they just want something that works), but surgery is deeper, channel count is still far below useful resolution (1,000–2,000 electrodes estimated needed), and no company has commercialized yet.3
- LGN route (phosphoenix): targets the retinotopic relay (LGN) — compact size, clinically accessible deep-brain target; retains intrinsic visual structure in that form and motion )P+M+K) streams are seperated in the laminar structure, allowing a cell-specific targetting without the need for current steering etc. There is a strong argument the LGN is a better target than the cortex…
What limits artificial vision (2025 review)
Kim & Seo’s survey flags the system-level constraints that apply across all sites:1
- Resolution ≠ channel count. More electrodes do not linearly raise acuity — current spread, retinal circuitry, and cortical integration impose a biological ceiling, and a pixel-size floor exists below which gains vanish. Tightening activation volumes (pillar electrodes, regional returns), spatiotemporal encoding, and task training are all needed to convert hardware pixels into usable vision.
- Device survival. The saline, micromotion environment is the defining constraint: active subretinal CMOS chips have failed post-implant where passive arrays endured. Hermetic packaging and interconnect reliability validated to 10-year targets is the stated priority; LCP, COC, and PFA films are the leading encapsulation candidates.
- Site trade-offs. Epiretinal: variable electrode–retina distance, heat at higher currents. Subretinal: low thresholds, but delicate detachment/reattachment surgery. Suprachoroidal: safer and more mechanically stable, but broader current spread. Optic-nerve and cortical routes bypass the diseased retina entirely — at greater invasiveness and device complexity.
- Priority list for the field: (1) packaging/interconnect reliability to 10-year targets; (2) constrained-spread electrodes and cell-type-aware encoding; (3) standardised real-world outcomes (navigation, scene parsing) beyond lab tasks; (4) human-factors integration of AR optics, power, and training.
Timeline snapshot (Aug 2026)
- 2000s–2010s: Retinal devices commercialized (Argus II 2011 CE/2013 FDA; Alpha AMS 2013 CE), both later abandoned.
- 2015: Nidek STS suprachoroidal–transretinal stimulation first-in-human pilot (49 channels; light perception, object localisation, mobility).1
- 2020: Chen et al. (Science) — 1024-channel cortical prosthesis in monkeys; monkey immediately recognized shapes/motion/letters.4
- 2021: First modern human cortical implant (96 electrodes, UMH Elche, Spain — patient Berna Gomez).
- 2023: First human with the Illinois Tech ICVP — wireless floating microelectrode modules for intracortical vision, with no trans-scalp wiring.1
- 2024: Science Corp. acquires PRIMA; Blindsight FDA Breakthrough designation.
- 2025: PRIMA NEJM (form vision in humans), Orion 5-year EFS results; Cortigent S-1 filed.
- 2026: PRIMA CE mark + EU commercial launch (Jul); Orion 6-year EFS results (NANS); ReVision Implant €4M + FDA Breakthrough + FIH approved; Phosphoenix fundraising + LGN pivot; Blindsight human trials expected ~2026. Adjacent smart-contact-lens: azalea-vision wins EIC Accelerator (Jul, €7.5M) to move its ALMA lens into clinical development.
Adjacent technology: smart contact lenses
Not all vision-restoration-adjacent work implants. Smart contact lenses are a fast-moving non-implantable category: the lens itself carries adaptive optics, microelectronics and connectivity to correct/adapt vision (clinically: presbyopia, keratoconus, irregular corneas, photophobia) and to sense tear biomarkers. The leading European example is azalea-vision (Belgium, imec/Ghent University spin-off, 2021), which won the EIC Accelerator in July 2026 (up to €7.5M: €2.5M grant + planned €5M EIC Fund equity) to take its ALMA lens into clinical development. Unlike prostheses, these devices correct existing optics rather than replacing photoreceptor/optic-path function — see azalea-vision for details and caveats.5
Adjacent modality: gene therapy and optogenetics
The non-device counterpart to prosthetics is gene therapy: one-time AAV-mediated delivery of a missing gene, a neuroprotective factor, a modifier gene, or a light-sensitive opsin into surviving retinal cells. It requires living target cells — photoreceptors/RPE for augmentation (e.g. Luxturna for RPE65-related disease), bipolar or ganglion cells for optogenetics — which makes it complementary to prostheses: implants can drive the retina or cortex even when photoreceptors are gone, while gene therapy can slow degeneration, restore function in still-viable cells, or re-sensitise the inner retina. The clinical landscape — Luxturna’s 2017 approval, late-stage XLRP/LCA1/XLRS/RP programs, the choroideremia and LHON failures, and the 2026 optogenetic readouts — is mapped on gene-therapy-vision-restoration. 6 7
Related pages
- retinal-prosthesis — retinal subcategory
- cortical-visual-prosthesis — cortex subcategory
- retinal-prosthesis-companies, cortical-visual-prosthesis-companies — schemas
- science-corp, phosphoenix, revision-implant, cortigent, neuralink, pieter-roelfsema
- visual-prosthesis-patents — patent-level IP landscape (per-patent summaries)
- azalea-vision — adjacent smart contact lens platform (non-implantable)
- gene-therapy-vision-restoration — gene-based restoration and optogenetics: the non-device counterpart to prosthetics
References
- Science Corp. NEJM/CE-mark releases (2025–2026); Vivani/Cortigent NANS 2026 release.
- Horizon Magazine (EU, 2023): NeuraViPeR & HyperStim projects; electrode-count estimates.
- Chen X, et al. Science 370(6521):1191-1196 (2020).
- Azalea Vision press release, Business Wire, 1 July 2026 (smart contact lens, EIC Accelerator).
- Kim J, Seo J-M. Advances in artificial vision systems: a comprehensive review of technologies, applications, and future directions. Biomed Eng Lett. 2025;15:1033–1050. DOI: 10.1007/s13534-025-00513-4 (open access; full text captured in
raw/papers/kim-2025-artificial-vision-review.md).1